Hydrops Fetalis (Fetal Hydrops)
Hydrops fetalis is an abnormal build-up of fluid in a baby’s body before birth, usually seen on an ultrasound scan. Fetal Hydrops have many possible causes, from blood and heart problems to genetic and immune conditions. Finding the cause early helps your fetal-medicine team plan monitoring, treatment and delivery. Contact your maternity unit if your baby’s movements reduce.

Seamless support from diagnosis to post treatment care
Overview
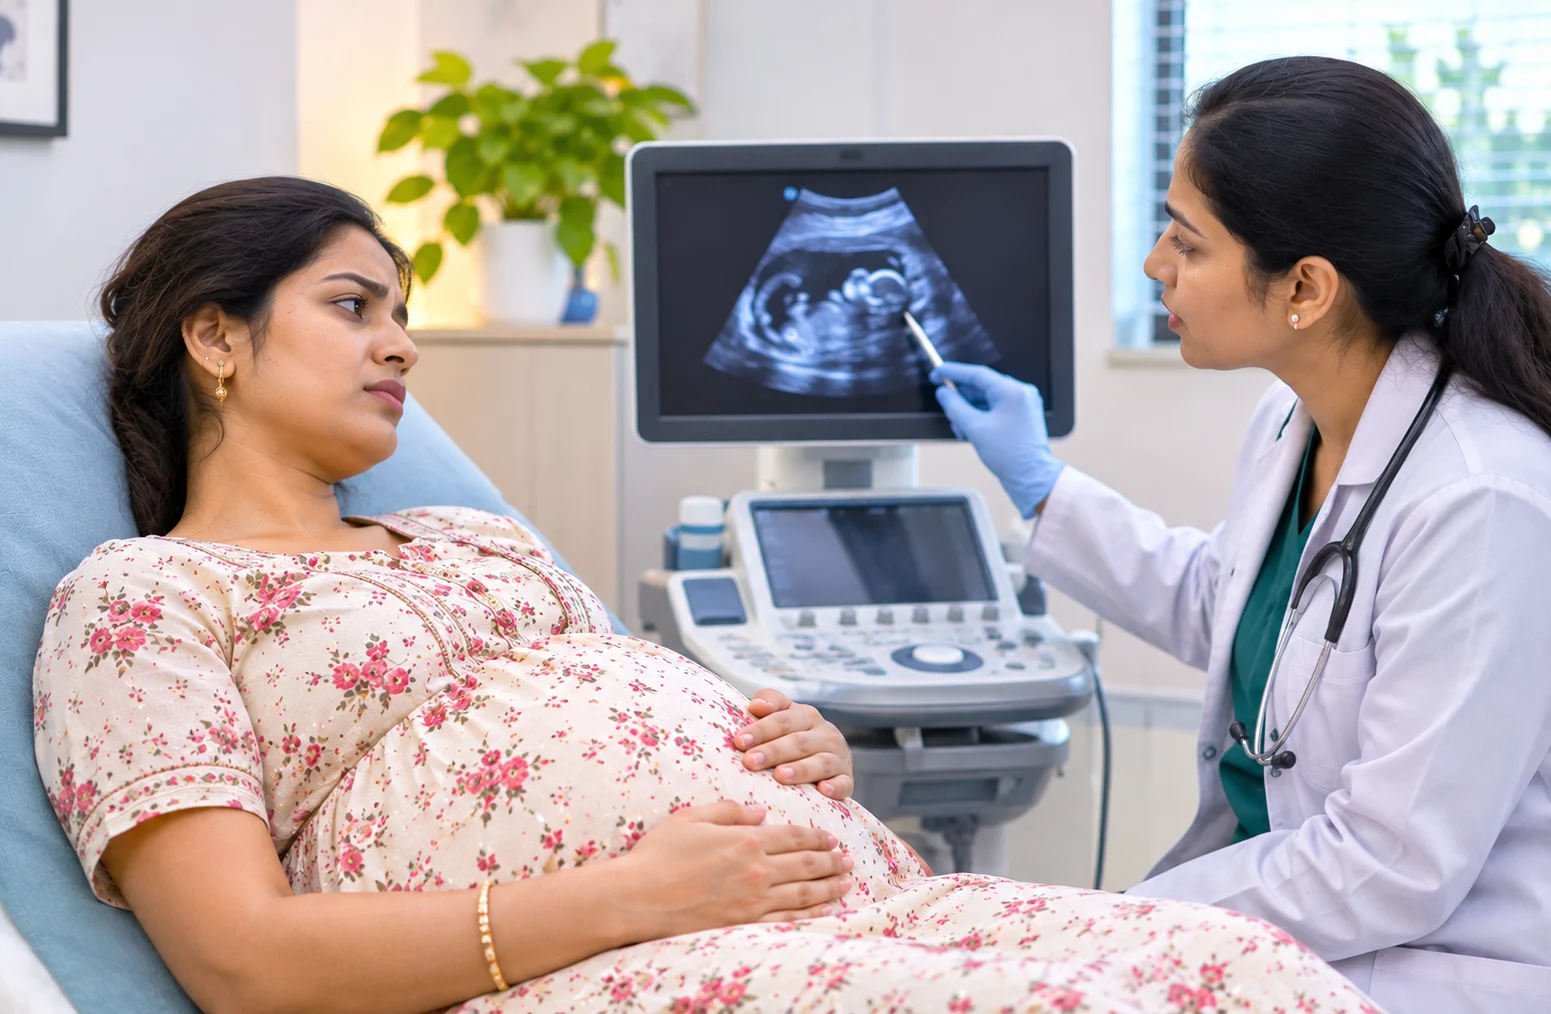
A finding on an ultrasound scan can bring many questions, especially when it means your baby needs closer monitoring during pregnancy. Hydrops fetalis is one such condition, involving an unusual build-up of fluid in different parts of a baby’s body before birth. While it can be serious, understanding the causes and available care options helps you and your medical team plan the next steps for your pregnancy.
What is Hydrops Fetalis?
Hydrops fetalis, also called fetal hydrops, is an abnormal build-up of fluid in two or more areas of a baby’s body before birth. Doctors usually detect it during an ultrasound scan, which suggests an underlying condition may be affecting the baby. It is not a diagnosis of the underlying cause itself.
Fluid may collect under the baby’s skin, around the lungs or heart, or inside the abdomen. The placenta may also become thicker than usual. The location and amount of fluid help doctors assess the condition and decide which tests are needed.
Hydrops fetalis can develop for several reasons, including problems affecting the baby’s heart, blood cells, genes or immune system. Identifying the cause is an important first step because some underlying conditions can be treated before birth.
How Does Hydrops Fetalis Develop in Pregnancy?
A baby's heart, blood vessels and lymphatic system help maintain a normal balance of fluid in the body. When an underlying condition affects blood circulation or fluid movement between the bloodstream and tissues, excess fluid can build up in different parts of the baby's body. This can lead to hydrops fetalis.
The fluid may collect in the following areas:
- Under the skin: Fluid causes swelling in the tissues beneath the skin.
- Inside the abdomen: Fluid collects around the baby’s abdominal organs. This is called ascites.
- Around the lungs: Fluid collects in the space around the lungs, called pleural effusion.
- Around the heart: Fluid builds up in the sac surrounding the heart. This is called pericardial effusion.
The placenta may also enlarge or thicken. Not every baby has fluid in all these areas. Doctors assess the ultrasound findings alongside other tests to understand what may be causing the fluid build-up and how it is affecting the baby.
Causes of Hydrops Fetalis
Hydrops fetalis is classified into two types based on what causes the fluid to build up in the baby's body: immune hydrops and non-immune hydrops. The main difference is whether the fluid build-up is caused by the mother's antibodies attacking the baby's red blood cells or by another underlying condition.
1. Immune Hydrops Fetalis
Immune hydrops fetalis occurs when antibodies in the mother's blood attack the baby's red blood cells and cause them to break down. This can lead to severe fetal anaemia (a shortage of red blood cells), making it harder for the baby's blood to carry enough oxygen. The baby's heart may then have to work harder, causing fluid to collect in different parts of the body.
One possible cause is Rh incompatibility, which can occur when an Rh-negative mother carries an Rh-positive baby and develops antibodies against the baby's red blood cells. Appropriate antenatal blood tests and anti-D injections for eligible Rh-negative mothers have made this type of hydrops much less common.
2. Non-Immune Hydrops Fetalis
Non-immune hydrops fetalis occurs when fluid accumulates due to conditions other than maternal antibodies attacking the baby's red blood cells. It accounts for most cases today. Important causes include:
- Cardiac conditions: Structural heart defects and abnormal heart rhythms, such as supraventricular tachycardia (SVT) and complete heart block, can affect blood circulation and cause fluid build-up. Cardiovascular abnormalities account for approximately 8–20% of cases.
- Chromosomal and genetic conditions: Turner syndrome, Down syndrome and genetic conditions such as Noonan syndrome (a RASopathy) can affect fetal development and lymphatic drainage. Genetic and syndromic conditions collectively account for approximately 19–53% of cases in published estimates.
- Blood disorders: Severe fetal anaemia can result from alpha-thalassaemia major (Hb Bart's hydrops fetalis), which is particularly relevant in South and Southeast Asian populations. G6PD deficiency is another rare, documented cause of severe fetal anaemia and hydrops.
- Infections during pregnancy: Parvovirus B19, cytomegalovirus (CMV), toxoplasmosis and syphilis can affect the baby's red blood cells, blood vessels or other organs. Infections account for approximately 7–8% of cases.
- Thoracic and lymphatic abnormalities: Congenital pulmonary airway malformation (CPAM), congenital diaphragmatic hernia and cystic hygroma can interfere with normal blood circulation or lymphatic drainage. Thoracic abnormalities account for approximately 5–6% and lymphatic abnormalities for 6–10% of cases.
- Placental and twin-related complications: Twin-to-twin transfusion syndrome (TTTS) can cause abnormal blood flow between twins, while placental chorioangioma (a non-cancerous placental tumour) can affect fetal circulation. TTTS accounts for approximately 4–5% and chorioangioma for around 2% of cases.
- Fetal tumours: Tumours such as sacrococcygeal teratoma (a growth near the baby's tailbone) can increase the demands on the baby's circulation and cause fluid accumulation.
- Metabolic and storage disorders: Inherited conditions affecting how the body processes or stores substances can interfere with organ function and fluid balance. These account for approximately 1–5% of cases in genetic studies.
Idiopathic hydrops fetalis refers to cases in which no underlying cause is identified despite detailed investigations. Published estimates vary; older systematic reviews reported approximately 18–20% of cases as idiopathic, with some clinical series reporting higher proportions.
Identifying the underlying cause helps the fetal-medicine team assess the baby's condition, determine whether treatment is possible and plan appropriate pregnancy care.
Risk Factors of Hydrops Fetalis
Hydrops fetalis can develop even when no risk factors are known. However, certain maternal, genetic and pregnancy-related circumstances may increase the likelihood of having a baby affected by the condition.
These include:
- Previous pregnancy affected by hydrops: A history of hydrops fetalis or severe fetal anaemia may indicate a risk of recurrence, particularly when an inherited condition is involved.
- Consanguinity: Pregnancy between close biological relatives can increase the likelihood of certain inherited genetic disorders.
- Both parents being thalassaemia carriers: When both parents carry alpha-thalassaemia gene changes associated with alpha-thalassaemia major, the baby may be at risk of Hb Bart's hydrops fetalis.
- RhD-negative mother without anti-D prophylaxis: An RhD-negative woman who has not received appropriate anti-D injections may develop antibodies against an RhD-positive baby's red blood cells, increasing the risk of immune hydrops.
- Twin pregnancy: Monochorionic twins (twins sharing a placenta) have a higher risk of complications such as twin-to-twin transfusion syndrome (TTTS), which can lead to hydrops.
Poorly controlled maternal diabetes is not a direct cause of hydrops fetalis, although it may contribute to certain pregnancy complications.
Having any of these risk factors does not mean your baby will develop hydrops fetalis. Preconception genetic counselling, appropriate antenatal blood tests and ultrasound examinations can help identify relevant risks early.
Signs and Symptoms of Hydrops Fetalis
Hydrops fetalis usually does not cause specific symptoms that the mother can identify at home. It is most often detected during an ultrasound scan, sometimes before any other signs are noticed.
Possible ultrasound findings include:
- Fluid under the baby's skin: Generalised swelling, also called fetal oedema.
- Fluid around the heart or lungs: These collections are known as pericardial and pleural effusions.
- Fluid inside the abdomen: This is called fetal ascites.
- Excess amniotic fluid: More fluid than usual surrounds the baby, a condition called polyhydramnios.
- An enlarged placenta: The placenta may appear thicker than expected on ultrasound.
Hydrops fetalis itself may not cause noticeable symptoms in the mother. However, some women develop mirror syndrome, a rare pregnancy complication in which the mother develops swelling due to fluid accumulation, often alongside fetal hydrops. Warning signs include sudden swelling, high blood pressure, headache and breathing difficulty. Seek urgent medical assessment if these symptoms develop.
If you notice reduced or unusual fetal movements, contact your maternity unit immediately rather than waiting for your next appointment.
Diagnosis of Hydrops Fetalis
Hydrops fetalis is diagnosed through a detailed ultrasound examination, followed by tests to identify its underlying cause. The assessment may include:
- Detailed fetal ultrasound: Confirms hydrops when abnormal fluid collections are present in at least two fetal compartments, such as under the skin, around the lungs or heart, or inside the abdomen. It also assesses fetal growth, the placenta and amniotic fluid.
- Middle cerebral artery (MCA) Doppler: Measures blood flow velocity in the baby's brain artery. Increased peak systolic velocity can indicate fetal anaemia.
- Fetal echocardiography: Examines the baby's heart structure, function and rhythm to identify cardiac abnormalities.
- Maternal blood tests: Blood group and antibody screening help identify RhD incompatibility and other red blood cell antibodies. A complete blood count (CBC), haemoglobin electrophoresis and thalassaemia screening may help identify inherited blood disorders.
- Tests for fetal-maternal blood mixing and infections: A Kleihauer-Betke test may detect fetal blood cells in the mother's circulation. Blood tests for parvovirus B19, TORCH infections and syphilis in women may help identify infections associated with hydrops.
- Maternal glucose testing: Helps assess whether diabetes may be contributing to pregnancy-related complications.
- Genetic testing: Amniocentesis may be offered for fetal karyotyping, chromosomal microarray or, when indicated, genetic sequencing such as exome testing to identify chromosomal and inherited conditions.
The fetal-medicine specialist selects investigations according to the ultrasound findings and medical history. Identifying the cause is important because some underlying conditions may be treatable during pregnancy.
Complications of Hydrops Fetalis
Hydrops fetalis can affect the baby's health and, in some cases, the mother's health. The possible complications depend on the cause, the amount of fluid and how the condition progresses.
For the Baby
- Strain on the heart: The heart may have to work harder to maintain circulation, particularly when fluid build-up is severe.
- Breathing difficulties after birth: Fluid around the lungs can interfere with normal lung expansion and may make breathing support necessary.
- Preterm birth: Early delivery may be recommended if continuing the pregnancy poses greater risks to the mother or baby than delivery.
- Other complications related to the underlying condition: The baby may need treatment for anaemia, a heart problem, an infection or another condition.
- Pregnancy loss: Severe hydrops can be life-threatening. The risk varies considerably depending on the underlying cause and the response to treatment.
For the Mother
- Excess amniotic fluid: An increased amount of fluid around the baby may cause abdominal discomfort and can contribute to pregnancy complications.
- Preeclampsia: Preeclampsia is a pregnancy-related condition involving high blood pressure that can affect the mother's organs. It may occur alongside a pregnancy complicated by hydrops.
- Mirror syndrome: This is a rare but serious condition in which the mother develops swelling alongside fluid build-up in the baby and sometimes the placenta. It may also involve high blood pressure and other complications.
Because hydrops can sometimes affect the mother's health as well as the baby's, regular assessment and an individualised care plan are important. Your team will explain the findings, discuss available options and monitor you for any signs that require a change in care.
Treatment Options and Care for Hydrops Fetalis
Treatment for hydrops fetalis depends on its underlying cause, the stage of pregnancy, the severity of the condition and the health of both mother and baby. Some causes can be treated before birth, while others have no established fetal treatment. A fetal-medicine specialist plans care based on the diagnosis and may recommend:
Treatment based on the underlying cause
- Immune hydrops and fetal anaemia: In cases caused by red blood cell antibodies, parvovirus B19 or other conditions leading to severe fetal anaemia, an intrauterine blood** **transfusion may be considered. Blood is given through the umbilical cord (intravascular transfusion) or, in selected cases, into the fetal abdomen (intraperitoneal transfusion). MCA peak systolic velocity (MCA-PSV) on Doppler ultrasound helps assess the risk of anaemia.
- Abnormal fetal heart rhythm: Arrhythmias such as supraventricular tachycardia may be treated with medicines given to the mother, including digoxin, flecainide or sotalol, with close monitoring.
- Fluid around the lungs: Large pleural effusions may require drainage (thoracentesis) or placement of a thoracoamniotic shunt to drain fluid into the amniotic cavity.
- Twin-to-twin transfusion syndrome (TTTS): In affected monochorionic twin pregnancies, fetoscopic laser treatment may seal abnormal blood-vessel connections on the shared placenta.
Pregnancy monitoring and delivery planning
- Regular monitoring: Ultrasound scans, Doppler studies and fetal echocardiography help assess the baby's condition and response to treatment.
- Antenatal corticosteroids: If preterm delivery is anticipated within seven days, corticosteroids may be given to support fetal lung maturity when neonatal resuscitation is planned.
- Planned delivery: Timing and mode of delivery depend on the baby's condition, the underlying cause and maternal health. Delivery should be planned at a tertiary-care centre with a NICU, an experienced neonatal team and facilities for newborn resuscitation and immediate care.
Counselling and decisions when fetal treatment is not possible
Some causes, including alpha-thalassaemia major (Hb Bart's hydrops fetalis) and certain severe fetal abnormalities, have no established fetal cure. The specialist team should discuss the likely outcome and available options with parents. These may include continuing the pregnancy with supportive care, pregnancy termination where legally permitted, or perinatal palliative care focused on the baby's comfort and the family's needs.
In India, the Medical Termination of Pregnancy (MTP) Act, 1971, as amended in 2021, permits termination beyond 24 weeks in cases of substantial fetal abnormalities diagnosed by a Medical Board, subject to applicable legal requirements. The care team can explain whether this provision applies to the individual circumstances.
Genetic counselling can help parents understand the risk of recurrence, particularly when an inherited condition is identified, and discuss options for future pregnancies.
What is the Prognosis (Outlook) for Hydrops Fetalis?
The outlook for hydrops depends on its underlying cause, severity, gestational age at diagnosis and response to treatment. Published studies report 36–68% survival among liveborn babies with non-immune hydrops fetalis (NIHF), although outcomes vary considerably.
Survival may be higher when the underlying cause is treatable:
- Fetal anaemia: Survival can reach approximately 80–85% following intrauterine transfusion for severe parvovirus B19-related anaemia. Outcomes can also exceed 80% in some cases of Rh-related fetal anaemia.
- Abnormal fetal heart rhythm: Many arrhythmias respond well to medicines, although hydrops increases the risk of complications and death.
- Chromosomal and structural abnormalities: These generally carry a poorer prognosis, particularly when severe abnormalities or early-onset hydrops are present.
Some babies who survive may experience developmental or neurological difficulties or require ongoing medical care. Long-term outcomes depend on the underlying cause, severity of hydrops and complications around birth.
The risk of recurrence in future pregnancies also depends on the cause. It is generally low for sporadic cases but higher with inherited conditions. For example, when both parents carry the gene variants responsible for alpha-thalassaemia major (Hb Bart's hydrops fetalis), each pregnancy has a 25% chance of being affected. Genetic counselling can help parents understand these risks.
The most reliable prognosis can be estimated after detailed scans and investigations identify the underlying cause. Your fetal-medicine team can explain the likely outcomes, available treatment options and delivery planning, while providing emotional support and counselling throughout the pregnancy.
What Questions Should I Ask My Doctor?
A diagnosis of hydrops fetalis can involve several investigations and decisions. Preparing a few questions before your appointment can help you understand the findings and take an active role in your care.
Cause and Testing Questions
- What has the ultrasound shown, and which parts of my baby's body are affected?
- Do you know what is causing the fluid build-up?
- Which tests do you recommend, and what will they tell us?
- Would genetic testing or amniocentesis be helpful in my situation?
- Is there a treatment available for the suspected cause?
Treatment and Support Questions
- What are the possible benefits and risks of treatment before birth?
- How often will I need scans or other monitoring?
- When might delivery be recommended, and how will it be planned?
- What kind of care might my baby need after birth?
- What support or counselling is available for me and my family?
Your doctor can help you identify the questions most relevant to your pregnancy. You may find it helpful to write down the answers or bring someone you trust to the appointment.
Can Hydrops Fetalis Be Prevented?
Hydrops fetalis cannot always be prevented because it can result from genetic conditions, structural abnormalities and other causes that are not under anyone's control. However, some of the conditions associated with hydrops can be identified early, and certain causes may be preventable or treatable.
The following measures can help where appropriate:
- Blood-group testing and anti-D prevention: Antenatal blood tests identify the mother's blood group and check for red blood cell antibodies. When indicated, anti-D immunoglobulin helps prevent Rh sensitisation in eligible Rh-negative mothers.
- Early and regular antenatal care: Routine appointments and recommended scans help identify certain fetal abnormalities and pregnancy complications.
- Infection assessment: Appropriate testing and medical advice can help identify infections that may affect the baby. Follow your healthcare team's advice on infection prevention during pregnancy.
- Pre-pregnancy and pregnancy care for existing conditions: Good management of known health conditions and genetic counselling when indicated can help assess risks and guide pregnancy planning.
These measures cannot prevent every cause of hydrops fetalis. If a cause is identified, your doctor can explain whether there are steps that may reduce the chance of recurrence in a future pregnancy.
Why Choose BirthRight by Rainbow Hospitals for Hydrops Fetalis Care?
At BirthRight by Rainbow Hospitals, we understand that a hydrops fetalis diagnosis can bring uncertainty and difficult questions. Our approach focuses on helping families understand the diagnosis, explore available options and receive coordinated care according to their individual needs.
- Specialist assessment and care planning: We help coordinate appropriate obstetric and fetal medicine assessment, where available, to investigate the fluid build-up and identify possible causes.
- Detailed pregnancy monitoring: Our care teams plan appropriate ultrasound examinations and follow-up according to the baby's condition and the stage of pregnancy, subject to services available at the chosen location.
- Individualised treatment discussions: We discuss the findings, explain potential treatment options and help families understand the benefits, limitations and risks of the recommended approach.
- Delivery planning and newborn care coordination: When delivery may be needed, we plan care based on the mother's health, the baby's condition, and the newborn support required. Relevant specialist teams and facilities depend on the hospital location.
- Guidance and emotional support: We recognise that families may need time, clear explanations and compassionate support while making decisions. We encourage open discussions with the treating team throughout pregnancy and after birth.
Contact your nearest Rainbow Hospital to learn about the fetal medicine specialist, obstetric and newborn-care services available for your specific needs.

Find a Doctor and Book Appointment Online
Meet our specialist doctors who bring together clinical expertise, compassion, and personalised care to support your health and well-being. Choose from 1,300+ specialists across our network and book an appointment with BirthRight and Rainbow Children Hospitals, offering 24*7 support to you and your family.

Dr. Pranathi Reddy A
Clinical Director – Obstetrics & Gynecology.
English,Hindi,Telugu Banjara Hills

Dr. Gauri Vinayak Dhamangaonkar
Senior Consultant - Fetal Medicine
15 Years English,Hindi,Marathi,Telugu Kondapur OP, Banjara Hills

Dr. Shruthi Reddy Poddutoor
Consultant Obstetrician, Gynecologist & Laparoscopic Surgeon
English,Telugu Banjara Hills

Dr. Himabindu Veerla
Consultant Obstetrician, Gynecologist & Laparoscopic Surgeon
English,Telugu Banjara Hills

Dr. Bhargavi Reddy K
Consultant - Obstetrics and Gynecology
10 Years English,Hindi,Telugu Banjara Hills, Attapur Clinic

Dr. Annie Pranutha P
Consultant Obstetrics and Gynecology
9 Years English,Hindi,Telugu Banjara Hills, Attapur Clinic

Dr. Sasikala Kola
Consultant Obstetrician & Gynecologist
English,Hindi,Telugu Banjara Hills

Dr. Atigadda Vijaya
Consultant - Obstetrics & Gynecology
Hindi,Telugu Banjara Hills, Himayatnagar, Attapur Clinic

Dr. Nishanth Reddy Inavolu
Visiting Consultant Physician and Diabetologist & Internal Medicine
English,Hindi,Telugu Banjara Hills, Himayatnagar

Dr. Tulika Tayal
Consultant - Fetal Medicine
English,Telugu Banjara Hills

Dr. M Prathyusha Reddy
Consultant Obstetrics & Gynecology
English,Telugu Banjara Hills

Dr. Nithya Narasimha Murthy
Consultant -Psychiatrist
English,Hindi,Telugu Kondapur OP, Banjara Hills, Child Development Centre - Banjarahills Rd No 10

Dr. Brundavani
Consultant - Nutritionist
English,Hindi,Telugu Kondapur OP, Hydernagar, Banjara Hills, Child Development Centre - Banjarahills Rd No 10

Dr. Niveditha Chalmeda
Consultant
English,Telugu Banjara Hills

Dr. Kirti Reddy Patlolla
Consultant Obstetrics and Gynaecology
English,Telugu Banjara Hills, Attapur Clinic

Dr. Tuheena Sharma
Consultant - Perinatal Physiotherapy
10 Years English,Telugu Banjara Hills

Dr. Aditi Shah
Consultant - Fetal Medicine
English,Telugu Banjara Hills

Dr. Swathi Naga Tulasi Rayapureddy
Lactation Consultant
8 Years English,Telugu Banjara Hills

Dr. Swetha Reddy. S
CONSULTANT PERINATAL PSYCHIATRIST AND WOMEN MENTAL HEALTH SPECIALIST
13 Years English,Hindi,Telugu Banjara Hills

Dr. Addu Kiranmayi
Chief Clinical Nutritionist and Lifestyle Medicine Consultant
15 Years English,Hindi,Telugu Himayatnagar, Banjara Hills

Dr. Palle Nalini Kumari
Lactation Consultant
17+ Years English,Hindi,Telugu Banjara Hills
Dr. Nazia Tabassum
Consultant - Breast, Plastic & Reconstructive Surgeon
9 Years English,Hindi,Telugu,Urdu Banjara Hills

Dr. Sruthi Cheera
Consultant Breast Surgeon
5 Years English,Hindi,Kannada,Telugu Banjara Hills

Dr. Supriya Reddy
Lactation Consultant
5 Years English,Hindi,Telugu Banjara Hills

Dr. Niraj Krishnamurthy Yanamandra
Senior Consultant Obstetrician & Gynaecologist, Laparoscopy & Hysteroscopy Surgeon
English,Hindi,Telugu Hydernagar, Banjara Hills

Dr. B. Rao Bahadur
Consultant – Obstetrician & Gynecologist, Laparoscopic ,& Hysteroscopic Surgeon
22 Years English,Hindi,Konkani,Marathi,Telugu Banjara Hills, Kondapur OP

Dr. Sneha Kulkarni
Consultant - Child, Adolescent & Adult Psychiatrist
10 Years English,Hindi,Kannada,Telugu Secunderabad, Banjara Hills, Child Development Centre - Banjarahills Rd No 10

Dr. Lavanya Janagama
Consultant – Obstetrics & Gynecology
10+ Years English Banjara HillsLeading Hospitals for Women Care
Rainbow Children's Hospital stands as a testament to the hospital's continual pursuit of excellence and innovation, providing specialized care for women and children


















chennai
Blogs
Discover our most recent health articles provided by our reliable experts.




What Are People Saying About Us
Embark on a journey of inspiration and hope with our patient success stories, complemented by informative videos from our dedicated doctors.


Media
 Common Gynaecological Surgeries to Fix Female Reproductive Issues
 Healthy Woman - Healthy World
 Healthier Women For a Healthier Future...
 Rainbow Children’s Hospital & BirthRight by Rainbow Launch Video Consultation Facilities
 Dr.Pranthi Reddy
 What is the use of that?
 Can you try this time?
 Pregnant Women are Not Unfit
 Declining Age of Menarche - A Matter of Concern
 Important Facts about Cervical Cancer
 Be careful before preempting
 Flu every month!
 Menstrual cramps
 Premature delivery
 Whether laughing or coughing...why?
 Multi - Tasking may be Cool but it's not Healthy
 Pregnant and Worried about COVID-19? Here's Everything you Need to know
 Video Consultation in Pandamic Situation for Pregnancy Women's
 Women.. Various types of cysts
 Recurrent Pregnancy Loss in Women
 Early Onset of Puberty: Causes, Symptoms and Treatment Options
Common Gynaecological Surgeries to Fix Female Reproductive Issues
Healthy Woman - Healthy World
Healthier Women For a Healthier Future...
FAQs
Can hydrops fetalis go away on its own?
What is the difference between immune and non-immune hydrops fetalis?
Can hydrops fetalis be detected at the 12-week or 20-week scan?
What is the outlook for my baby, and can the baby be born healthy?
Can a blood transfusion before birth treat hydrops fetalis?
How is hydrops fetalis different from normal swelling or extra fluid in a baby?
Can I have a normal delivery with hydrops fetalis?
Will hydrops fetalis happen again in my next pregnancy?
Did I do something to cause hydrops fetalis?
Will I need genetic testing after hydrops fetalis is found?
Is hydrops fetalis fatal?
What causes hydrops fetalis in the third trimester?
Can hydrops fetalis be reversed?
What is the link between hydrops fetalis and thalassaemia?
Can parvovirus B19 infection cause hydrops fetalis?
Quick Links
Free Calculators to Track and Predict your Pregnancy
Gynecologist in Other Locations
Women's Health Conditions We Treat
- Mastitis (Breast Infection)
- PCOS (Polycystic Ovary Syndrome)
- Uterine Fibroids (Leiomyomas)
- Recurrent Pregnancy Loss
- Blocked Fallopian Tubes (Fallopian Tube Obstruction)
- Gestational Diabetes in Pregnancy
- Incompetent Cervix (Cervical Insufficiency)
- COVID-19 in Pregnancy
- Cytomegalovirus (CMV) in Pregnancy
- HELLP Syndrome
- Luteal Phase Defect
- Vasa Previa
- Listeria in Pregnancy
- Placenta Previa
- Endometrial Polyps (Uterine Polyps)
- Congenital Heart Disease in Pregnancy
- Hyperemesis Gravidarum (Severe Morning Sickness)
- Preeclampsia (toxemia)
- Fetal Distress (Non-Reassuring Fetal Status)
- Postpartum Haemorrhage (PPH)
- Placental Abruption (Abruptio Placentae)
- Placenta Accreta
- Postpartum Depression (PPD)
- Rhesus (Rh) Incompatibility
- Syphilis in Women
- Thalassemia in Pregnancy
- Gestational Thrombocytopenia
- Diabetes in Pregnancy
- Uterine Rupture
- Migraine in Pregnancy