Fetal Distress (Non-Reassuring Fetal Status)
Fetal distress, also called non-reassuring fetal status, is a term for signs that your baby may not be receiving enough oxygen in pregnancy or during labour. It is usually found through changes in the baby’s heart rate on a CTG, or when movements reduce. An abnormal pattern does not always mean harm, and prompt assessment lets your team correct the cause or arrange a safe delivery.

Seamless support from diagnosis to post treatment care
Overview
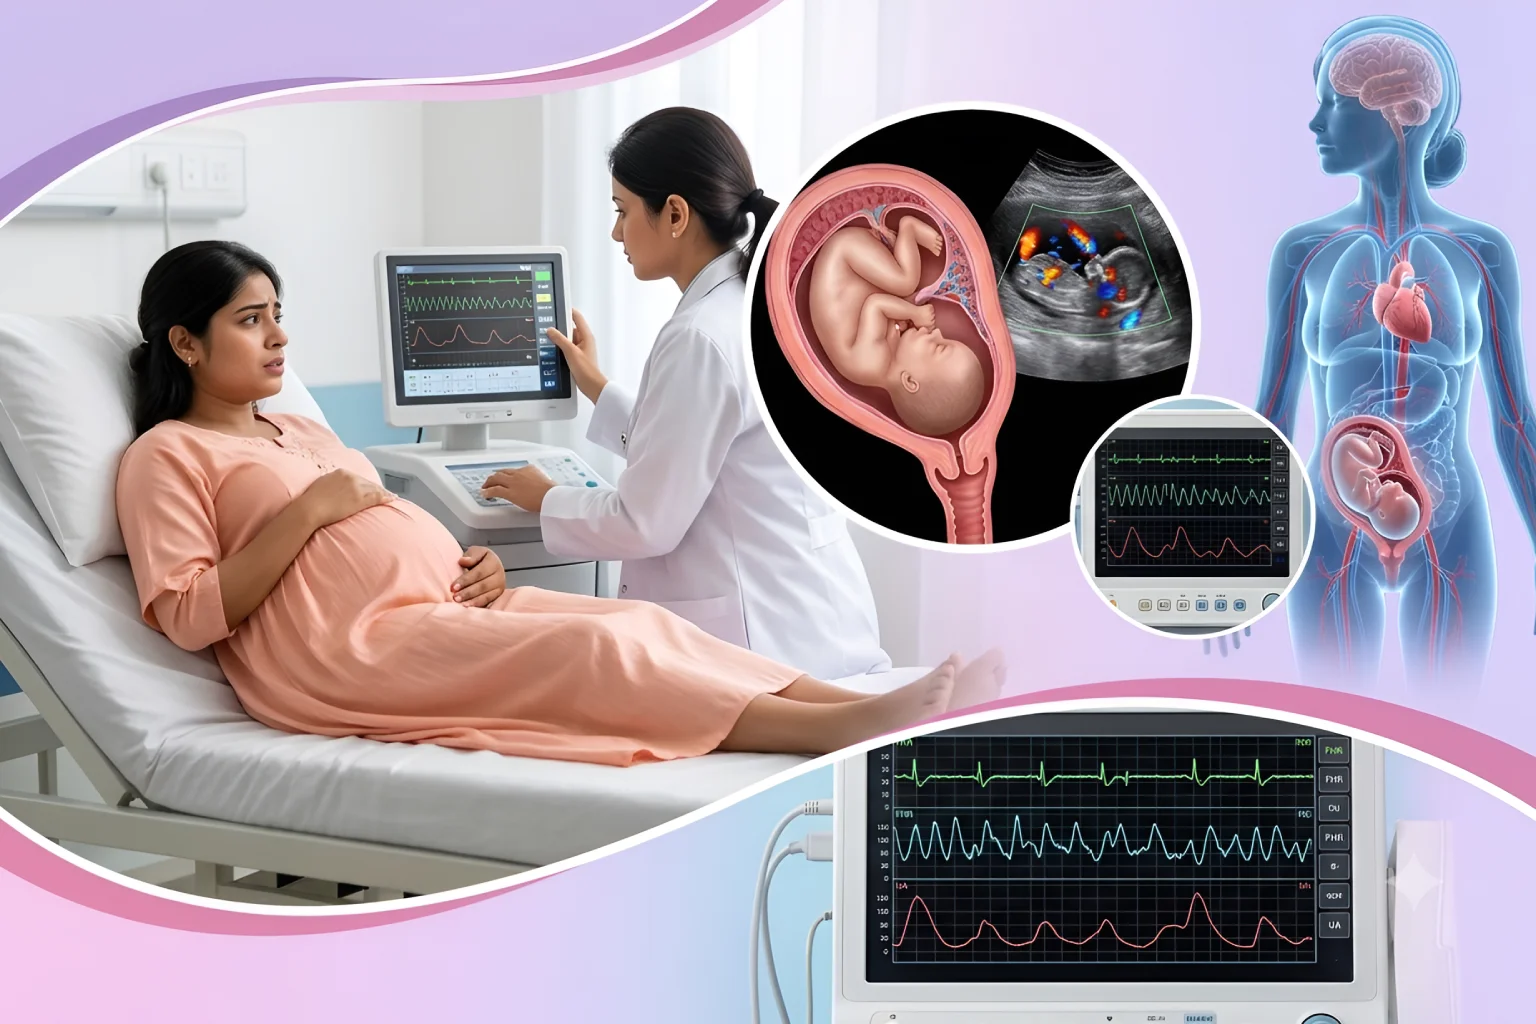
During pregnancy and labour, your baby's movements and heart rate provide important information about their wellbeing. If your healthcare team notices a change, they may recommend closer monitoring or additional checks to understand what is happening. This can feel concerning, especially as you prepare to meet your baby, but a change in the heart rate does not always mean something is wrong.
Recognising these changes and responding promptly helps your medical team decide whether your baby needs additional support or an earlier delivery. Knowing what fetal distress means, how it is detected and what happens if it is suspected can help you feel more informed and prepared.
What is Fetal Distress?
Fetal distress is a commonly used term for signs that a baby may not be receiving enough oxygen or may be struggling to cope during pregnancy or labour. Doctors increasingly use terms such as non-reassuring fetal status or suspected fetal compromise to describe these findings.
Fetal distress is most often suspected through cardiotocography (CTG), which monitors the baby's heart rate and the mother's contractions. A normal fetal heart rate is generally 110–160 beats per minute. Persistent changes in the baseline rate, reduced variability or repeated drops in heart rate may indicate that the baby needs further assessment.
Abnormal CTG patterns are relatively common, but severe fetal metabolic acidosis is much less common, occurring in approximately 0.26%–1.3% of newborns. Severe metabolic acidosis is generally defined by an umbilical artery pH below 7.00 with a base deficit of 12 mmol/L or more. Therefore, an abnormal CTG does not necessarily mean the baby has suffered oxygen deprivation.
If monitoring shows concerning patterns, your obstetrician will assess your baby's condition and decide whether closer monitoring, interventions or prompt delivery are needed.
How Fetal Distress Affects Your Baby’s Oxygen Supply?
Your baby receives oxygen from your blood through the placenta, an organ that develops during pregnancy, and the umbilical cord, which connects the baby to the placenta. During labour, contractions temporarily reduce blood flow through the placenta. Most healthy babies tolerate these changes well because they have enough reserve to cope with them.
However, if blood flow or oxygen delivery is reduced for too long, or if the baby has difficulty coping with contractions, their heart rate may change. These changes can sometimes indicate that the baby needs additional support.
Fetal heart rate monitoring helps your medical team recognise these patterns. The team considers the baby's heart rate alongside your contractions, blood pressure, medical history and other clinical findings to decide whether intervention is needed.
Causes of Fetal Distress
Fetal distress can develop when the baby's oxygen supply is reduced or the baby struggles to tolerate labour. Some causes are temporary and reversible, while others require urgent intervention.
Common causes include:
- Uterine hyperstimulation: Oxytocin or prostaglandins used to induce labour may cause overly frequent contractions, leaving less time for the baby to recover.
- Placental abruption: Early separation of the placenta from the uterus can reduce the baby's oxygen supply.
- Umbilical cord compression or prolapse: Pressure on the cord can restrict blood flow and oxygen delivery to the baby.
- Maternal hypotension or low oxygen levels: A sudden drop in the mother's blood pressure, sometimes following an epidural or lying flat on her back, can reduce placental blood flow.
- Maternal fever or infection: Infections such as chorioamnionitis can cause changes in the baby's heart rate.
- Uterine rupture: A tear in the uterine wall can interrupt the baby's oxygen supply and requires emergency care.
- Fetal anaemia: Low red blood cell levels can reduce oxygen delivery to the baby's tissues.
- Prolonged second stage of labour: A lengthy pushing stage may increase the risk of fetal compromise.
- Meconium-stained amniotic fluid: The presence of the baby's first stool in the fluid may indicate possible fetal compromise, particularly alongside abnormal heart rate patterns.
Some causes, such as excessive contractions and maternal hypotension, may improve with prompt treatment. Others, such as cord prolapse, placental abruption and uterine rupture, may require emergency delivery.
Risk Factors for Fetal Distress
Fetal distress can occur without known risk factors. However, certain maternal and pregnancy-related conditions can increase the likelihood of fetal compromise.
These include:
- Fetal growth restriction: Poor fetal growth may indicate problems with placental function.
- Low amniotic fluid: Reduced fluid can increase the risk of umbilical cord compression.
- Post-term pregnancy: Pregnancy extending beyond 42 weeks may be associated with reduced placental function.
- Multiple pregnancy: Carrying twins or more babies increases the likelihood of pregnancy and labour complications.
- Maternal health conditions: Diabetes, hypertension, heart disease and kidney disease may affect placental function and fetal wellbeing.
- Pre-eclampsia: Pregnancy-related high blood pressure can affect blood flow through the placenta.
- Previous caesarean or uterine surgery: A uterine scar may increase the risk of uterine rupture during labour.
Having these risk factors does not mean your baby will develop fetal distress. Your obstetrician will recommend monitoring based on your individual pregnancy and medical history.
Signs & Symptoms of Fetal Distress
Fetal distress usually cannot be identified by how you feel alone. Your healthcare team usually detects the most concerning signs through heart rate monitoring. However, changes in your baby's movements during pregnancy may indicate the need for an assessment.
Important signs include:
- An unusually slow or persistently fast heart rate: A heart rate outside the expected range may require further assessment, depending on how long the change lasts and the overall pattern.
- Repeated heart rate drops: The baby's heart rate may fall during or after contractions. Repeated drops, particularly when recovery is delayed, can indicate that the baby is having difficulty coping with labour.
- Reduced or changed fetal movements: If your baby moves less than usual, stops moving or shows a noticeable change in their usual movement pattern, contact your maternity unit or obstetrician immediately.
You cannot reliably assess your baby's oxygen supply by feeling their movements or checking their heartbeat at home. If you notice reduced or changed movements, do not wait until the next day or rely on a home Doppler device for reassurance. Seek prompt medical assessment, even if your previous check-up was normal.
If you are already in labour and your team identifies a concerning heart rate pattern, they will explain what they are seeing and what steps may be needed.
Diagnosis of Fetal Distress
Doctors assess suspected fetal distress using fetal heart rate monitoring, maternal observations and other tests, depending on the stage of pregnancy and labour.
1. Fetal Heart Rate Monitoring
- Intermittent auscultation: For low-risk labour, the doctor or midwife periodically checks the baby's heartbeat using a handheld Doppler or Pinard stethoscope.
- Continuous cardiotocography (CTG): CTG records the baby's heart rate and uterine contractions continuously, particularly when risk factors or concerning heart rate changes are present.
2. CTG Pattern Assessment
Doctors assess four important features of the CTG trace:
- Baseline heart rate: Normally 110–160 beats per minute.
- Variability: Normal fluctuations in the heart rate, generally 5–25 beats per minute.
- Accelerations: Temporary increases in heart rate, generally reassuring when present.
- Decelerations: Temporary drops in heart rate. Repeated late decelerations, concerning variable decelerations and prolonged decelerations may indicate fetal compromise.
CTG traces are classified using systems such as the NICE normal, suspicious and pathological categories or the three-tier Category I, II and III system.
3. Additional Tests
Depending on the clinical situation, doctors may recommend:
- Ultrasound and Doppler: Assess fetal growth, amniotic fluid levels and blood flow through the placenta and umbilical cord during pregnancy.
- Fetal scalp blood sampling: Where available and appropriate, a small blood sample may be tested for pH or lactate to assess possible fetal acidosis during labour.
- Assessment of amniotic fluid: Meconium staining may prompt closer monitoring and further assessment.
Note: CTG has a high false-positive rate, meaning an abnormal pattern does not necessarily indicate oxygen deprivation or injury. Doctors interpret the trace alongside the mother's condition, labour progress and other clinical findings before deciding on treatment or delivery.
Complications of Untreated Fetal Distress
Many babies with concerning heart rate patterns are delivered safely, and an abnormal pattern does not automatically mean that injury has occurred. However, if a baby experiences a severe or prolonged lack of oxygen, complications can develop.
Possible complications include:
- Hypoxic-ischaemic encephalopathy (HIE): A type of brain injury caused by reduced oxygen and blood flow to the brain around the time of birth.
- Seizures in the newborn: Severe oxygen deprivation can sometimes affect the brain and cause seizures after birth.
- Long-term neurological difficulties: In some cases of significant oxygen deprivation, a child may develop lasting difficulties with movement, learning or development. Cerebral palsy, a condition affecting movement and posture, is one possible outcome in some cases.
- Stillbirth: Severe, prolonged oxygen deprivation can sometimes result in the baby's death before birth, although this is not the usual outcome when concerns are recognised and managed promptly.
The likelihood of these complications depends on the cause, severity and duration of the problem, as well as the baby's condition and how quickly appropriate care is provided. Monitoring during labour helps the medical team identify concerning changes and respond when necessary.
If your baby needs additional assessment after birth, the neonatal team may examine them, monitor their condition and provide treatment according to their needs. A concerning heart rate pattern alone does not establish that your baby has sustained an injury.
Treatment Options for Fetal Distress
Treatment depends on the baby's heart rate pattern, the suspected cause, the stage of labour and the mother's condition. Doctors first try to correct reversible causes. If the baby's condition remains concerning, prompt delivery may be necessary.
For Early or Mild Signs
Your healthcare team may use the following measures to improve the baby's oxygen supply:
- Changing your position: Turning onto your left side can improve blood flow to the placenta and relieve pressure on the umbilical cord.
- Stopping oxytocin: If contractions are too frequent, your team may reduce or stop oxytocin to allow the baby more time to recover between contractions.
- Giving intravenous fluids: An IV fluid bolus may be given if your blood pressure is low, particularly following an epidural.
- Giving medication to relax the uterus: A medicine such as terbutaline may be used if contractions remain too frequent.
- Checking for cord prolapse: A vaginal examination may be performed if cord prolapse is suspected, particularly following a sudden drop in the baby's heart rate.
- Amnioinfusion: In selected cases, fluid may be introduced into the uterus to reduce umbilical cord compression. It is not a routine treatment for fetal distress.
Maternal oxygen is not routinely recommended for abnormal fetal heart rate patterns if the mother's oxygen levels are normal.
For Severe or Prolonged Distress
If the baby's heart rate remains seriously abnormal despite initial measures, your obstetrician may recommend prompt delivery.
- Assisted vaginal birth: Forceps or a vacuum device may be used if the cervix is fully dilated and the baby's position allows safe, rapid delivery.
- Emergency caesarean birth: A caesarean may be necessary if vaginal delivery is not possible or would take too long.
In an emergency, delivery is arranged as quickly as safely possible. Many hospitals use a 30-minute decision-to-delivery target for the most urgent category of caesarean births, although this is not a universal deadline and some situations require faster intervention.
Care After Birth
If fetal distress was suspected, the neonatal team may assess the baby immediately after delivery. Umbilical cord blood gas testing may help identify whether significant oxygen deprivation or acidosis occurred. Babies showing signs of moderate-to-severe hypoxic-ischaemic encephalopathy (HIE) may be assessed for therapeutic cooling, which should begin within six hours of birth.
Not every suspected case of fetal distress requires a caesarean. If the heart rate improves and the baby is assessed as coping well, labour may continue with appropriate monitoring.
What is the Prognosis (Outlook) for Fetal Distress?
The outlook is generally reassuring when fetal distress is recognised and managed promptly. Most babies with abnormal CTG patterns are born without serious injury because these patterns have a high false-positive rate and do not necessarily indicate oxygen deprivation.
Hypoxic-ischaemic encephalopathy (HIE), a type of brain injury caused by reduced oxygen and blood supply, affects approximately 1–3 in every 1,000 term newborns. Most cases of cerebral palsy are also not caused by oxygen deprivation during labour; one systematic review attributed only about 14.5% of cerebral palsy cases to intrapartum hypoxia.
The outcome depends on how severe and prolonged the oxygen deprivation is and how quickly it is addressed. Timely intervention reduces the risk of serious complications, including stillbirth and neonatal death. Early recognition and treatment generally offer a better outlook than delayed intervention.
Babies suspected of having HIE receive a detailed newborn neurological assessment. Those with moderate-to-severe HIE may benefit from therapeutic hypothermia (controlled cooling), started within six hours of birth and continued for 72 hours. Follow-up assessments help monitor their neurological development and identify any delays early.
What Questions Should I Ask My Gynecologists?
It is natural to have questions if your pregnancy requires additional monitoring or your baby's heart rate changes during labour. Asking your gynecologists to explain the findings and available options can help you understand the care being recommended.
Monitoring Questions
- How will my baby's heart rate be monitored during labour?
- Do my pregnancy or medical history mean I need continuous monitoring?
- What does the current heart rate pattern indicate?
- Which changes in my baby's movements should I report immediately?
Intervention Questions
- What could be causing the changes in my baby's heart rate?
- Which measures can help improve the heart rate pattern?
- Under what circumstances might I need an assisted vaginal birth or a caesarean?
- Will a paediatrician or neonatal specialist assess my baby after birth if needed?
You do not need to remember every question or understand every medical term. Ask your healthcare team to explain anything that is unclear. If an urgent intervention is required, the team may need to act quickly while providing as much explanation as the situation allows.
Prevention & Lifestyle Tips for Fetal Distress
Fetal distress cannot always be prevented. It may develop suddenly during labour, even when the pregnancy has been progressing normally. However, attending antenatal appointments, managing existing health conditions and reporting changes promptly can help your healthcare team identify concerns and plan appropriate care.
The following steps can support your pregnancy and your baby's wellbeing:
- Attend your antenatal appointments: Regular check-ups help your obstetrician monitor your health, your baby's growth and any conditions that may affect pregnancy.
- Manage existing health conditions: Follow your healthcare team's advice for conditions such as diabetes or high blood pressure, and attend recommended follow-up appointments.
- Know your baby's usual movement pattern: Become familiar with your baby's normal movements. Contact your maternity unit immediately if movements decrease, stop or change noticeably.
- Report vaginal bleeding or fluid leakage: These symptoms may need prompt assessment, particularly if they occur before labour or are accompanied by pain or other changes.
- Seek advice about unusual contractions: Contact your maternity team if contractions are unusually frequent, continuous or concerning, especially if you are not yet at term.
- Follow your individual monitoring plan: If your obstetrician recommends additional scans or closer monitoring because of a pregnancy-related condition, attend the recommended appointments.
These steps cannot guarantee that fetal distress will not occur, but they help ensure that changes in your health or your baby's wellbeing are assessed in good time. If you notice reduced fetal movements or another concerning symptom, seek medical advice rather than trying to manage it at home.
Why Choose BirthRight by Rainbow Hospitals for Fetal Distress Care?
BirthRight by Rainbow Hospitals brings together obstetricians, newborn specialists and labour-ward teams in one place, backed by three decades of expertise in women’s and children’s health. Fetal distress can arise quickly, so our labour-and-delivery units use continuous monitoring and are ready to act without delay. From close monitoring to 24/7 emergency caesarean readiness, your baby’s wellbeing is watched at every step.
If your baby needs help after birth, a neonatal team and a well-equipped unit are on hand under the same roof. This means that monitoring, delivery and newborn care all happen in one place. The aim throughout is a safe birth and a healthy baby.
Disclaimer
This article is intended for general educational purposes and does not replace individual medical advice, diagnosis or treatment. Fetal distress requires assessment by qualified healthcare professionals. If your baby is moving less than usual or has stopped moving, contact your maternity unit or obstetrician immediately. Seek urgent medical attention for significant vaginal bleeding, severe abdominal pain or other emergency symptoms.

Find a Doctor and Book Appointment Online
Meet our specialist doctors who bring together clinical expertise, compassion, and personalised care to support your health and well-being. Choose from 1,300+ specialists across our network and book an appointment with BirthRight and Rainbow Children Hospitals, offering 24*7 support to you and your family.

Dr. Pranathi Reddy A
Clinical Director – Obstetrics & Gynecology.
English,Hindi,Telugu Banjara Hills

Dr. Gauri Vinayak Dhamangaonkar
Senior Consultant - Fetal Medicine
15 Years English,Hindi,Marathi,Telugu Kondapur OP, Banjara Hills

Dr. Shruthi Reddy Poddutoor
Consultant Obstetrician, Gynecologist & Laparoscopic Surgeon
English,Telugu Banjara Hills

Dr. Himabindu Veerla
Consultant Obstetrician, Gynecologist & Laparoscopic Surgeon
English,Telugu Banjara Hills

Dr. Bhargavi Reddy K
Consultant - Obstetrics and Gynecology
10 Years English,Hindi,Telugu Banjara Hills, Attapur Clinic

Dr. Annie Pranutha P
Consultant Obstetrics and Gynecology
9 Years English,Hindi,Telugu Banjara Hills, Attapur Clinic

Dr. Sasikala Kola
Consultant Obstetrician & Gynecologist
English,Hindi,Telugu Banjara Hills

Dr. Atigadda Vijaya
Consultant - Obstetrics & Gynecology
Hindi,Telugu Banjara Hills, Himayatnagar, Attapur Clinic

Dr. Nishanth Reddy Inavolu
Visiting Consultant Physician and Diabetologist & Internal Medicine
English,Hindi,Telugu Banjara Hills, Himayatnagar

Dr. Tulika Tayal
Consultant - Fetal Medicine
English,Telugu Banjara Hills

Dr. M Prathyusha Reddy
Consultant Obstetrics & Gynecology
English,Telugu Banjara Hills

Dr. Nithya Narasimha Murthy
Consultant -Psychiatrist
English,Hindi,Telugu Kondapur OP, Banjara Hills, Child Development Centre - Banjarahills Rd No 10

Dr. Brundavani
Consultant - Nutritionist
English,Hindi,Telugu Kondapur OP, Hydernagar, Banjara Hills, Child Development Centre - Banjarahills Rd No 10

Dr. Niveditha Chalmeda
Consultant
English,Telugu Banjara Hills

Dr. Kirti Reddy Patlolla
Consultant Obstetrics and Gynaecology
English,Telugu Banjara Hills, Attapur Clinic

Dr. Tuheena Sharma
Consultant - Perinatal Physiotherapy
10 Years English,Telugu Banjara Hills

Dr. Aditi Shah
Consultant - Fetal Medicine
English,Telugu Banjara Hills

Dr. Swathi Naga Tulasi Rayapureddy
Lactation Consultant
8 Years English,Telugu Banjara Hills

Dr. Swetha Reddy. S
CONSULTANT PERINATAL PSYCHIATRIST AND WOMEN MENTAL HEALTH SPECIALIST
13 Years English,Hindi,Telugu Banjara Hills

Dr. Addu Kiranmayi
Chief Clinical Nutritionist and Lifestyle Medicine Consultant
15 Years English,Hindi,Telugu Himayatnagar, Banjara Hills

Dr. Palle Nalini Kumari
Lactation Consultant
17+ Years English,Hindi,Telugu Banjara Hills
Dr. Nazia Tabassum
Consultant - Breast, Plastic & Reconstructive Surgeon
9 Years English,Hindi,Telugu,Urdu Banjara Hills

Dr. Sruthi Cheera
Consultant Breast Surgeon
5 Years English,Hindi,Kannada,Telugu Banjara Hills

Dr. Supriya Reddy
Lactation Consultant
5 Years English,Hindi,Telugu Banjara Hills

Dr. Niraj Krishnamurthy Yanamandra
Senior Consultant Obstetrician & Gynaecologist, Laparoscopy & Hysteroscopy Surgeon
English,Hindi,Telugu Hydernagar, Banjara Hills

Dr. B. Rao Bahadur
Consultant – Obstetrician & Gynecologist, Laparoscopic ,& Hysteroscopic Surgeon
22 Years English,Hindi,Konkani,Marathi,Telugu Banjara Hills, Kondapur OP

Dr. Sneha Kulkarni
Consultant - Child, Adolescent & Adult Psychiatrist
10 Years English,Hindi,Kannada,Telugu Secunderabad, Banjara Hills, Child Development Centre - Banjarahills Rd No 10

Dr. Lavanya Janagama
Consultant – Obstetrics & Gynecology
10+ Years English Banjara HillsLeading Hospitals for Women Care
Rainbow Children's Hospital stands as a testament to the hospital's continual pursuit of excellence and innovation, providing specialized care for women and children


















chennai
Blogs
Discover our most recent health articles provided by our reliable experts.




What Are People Saying About Us
Embark on a journey of inspiration and hope with our patient success stories, complemented by informative videos from our dedicated doctors.


Media
 Common Gynaecological Surgeries to Fix Female Reproductive Issues
 Healthy Woman - Healthy World
 Healthier Women For a Healthier Future...
 Rainbow Children’s Hospital & BirthRight by Rainbow Launch Video Consultation Facilities
 Dr.Pranthi Reddy
 What is the use of that?
 Can you try this time?
 Pregnant Women are Not Unfit
 Declining Age of Menarche - A Matter of Concern
 Important Facts about Cervical Cancer
 Be careful before preempting
 Flu every month!
 Menstrual cramps
 Premature delivery
 Whether laughing or coughing...why?
 Multi - Tasking may be Cool but it's not Healthy
 Pregnant and Worried about COVID-19? Here's Everything you Need to know
 Video Consultation in Pandamic Situation for Pregnancy Women's
 Women.. Various types of cysts
 Recurrent Pregnancy Loss in Women
 Early Onset of Puberty: Causes, Symptoms and Treatment Options
Common Gynaecological Surgeries to Fix Female Reproductive Issues
Healthy Woman - Healthy World
Healthier Women For a Healthier Future...
FAQs
How can I track my baby’s movements at home to check for fetal distress?
Does fetal distress always mean an emergency C-section is needed?
Can fetal distress happen even with a low-risk, healthy pregnancy?
Will my baby have long-term problems if fetal distress is caught and treated quickly?
Is fetal distress more common with induced labour?
Can stress or anxiety cause fetal distress?
How is fetal distress different from a normal, brief heart rate dip during contractions?
Can I have a vaginal delivery after fetal distress was suspected in labour?
Can fetal distress happen again in a future pregnancy?
Can too much movement mean fetal distress?
What is the modern medical term for fetal distress?
Quick Links
Free Calculators to Track and Predict your Pregnancy
Understand your cycle and plan ahead with these quick, free fertility tools.
Gynecologist in Other Locations
Women's Health Conditions We Treat
- Mastitis (Breast Infection)
- PCOS (Polycystic Ovary Syndrome)
- Uterine Fibroids (Leiomyomas)
- Recurrent Pregnancy Loss
- Blocked Fallopian Tubes (Fallopian Tube Obstruction)
- Gestational Diabetes in Pregnancy
- Incompetent Cervix (Cervical Insufficiency)
- COVID-19 in Pregnancy
- Cytomegalovirus (CMV) in Pregnancy
- HELLP Syndrome
- Luteal Phase Defect
- Vasa Previa
- Listeria in Pregnancy
- Placenta Previa
- Endometrial Polyps (Uterine Polyps)
- Congenital Heart Disease in Pregnancy
- Hyperemesis Gravidarum (Severe Morning Sickness)
- Preeclampsia (toxemia)